Pancolitis describes inflammation involving the entire colon (large intestine). Most commonly, the term refers to ulcerative pancolitis, meaning ulcerative colitis that extends continuously from the rectum through the entire colon. It is therefore not usually considered a separate disease from ulcerative colitis; rather, it describes the extent of the disease.
Ulcerative colitis (UC) is a chronic inflammatory bowel disease (IBD) in which inflammation and ulceration affect the innermost lining of the colon and rectum. In UC, inflammation typically begins in the rectum and extends upward through the colon in a continuous pattern rather than leaving normal “skip areas” between inflamed sections.
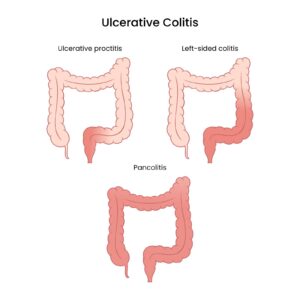
The different patterns can therefore be thought of approximately as:
Proctitis → rectum only
Left-sided colitis → rectum + left side of colon
Pancolitis → entire colon involved
One important technical point for your eventual protocol: “pancolitis” literally describes inflammation throughout the colon and is not always caused by ulcerative colitis. Other diseases, including Crohn’s disease, certain infections such as C. difficile, reduced blood supply, some medicines/radiation, and other conditions can produce inflammation involving the whole colon. Therefore, a protocol should distinguish confirmed ulcerative pancolitis from “pancolitis” as a general finding.
Because pancolitis involves such a large surface area of the colon, symptoms may be more extensive than in disease confined to a small section.
Diarrhea is one of the hallmark symptoms. During active disease, bowel movements can become very frequent, and stools may be loose or watery.
The inflamed colon is less able to perform its normal functions effectively, including water handling, which contributes to diarrhea.
Inflammation damages the delicate inner lining of the colon and can produce ulceration and bleeding.
A person may therefore notice:
• bright or darker red blood in stool
• blood mixed with diarrhea
• blood and mucus together
• rectal bleeding
Bloody diarrhea is particularly characteristic of active ulcerative colitis.
The inflamed and ulcerated bowel lining may produce increased mucus, and stools can contain mucus or pus, sometimes together with blood.
Inflammation and increased bowel activity can cause:
• abdominal cramping
• lower abdominal discomfort
• pain before bowel movements
• generalized abdominal pain
Pancolitis may produce substantial abdominal cramping because inflammation extends throughout the colon.
Patients can experience a sudden, intense need to empty the bowel and may have difficulty delaying a bowel movement.
This can become one of the most disruptive symptoms of active disease.
Tenesmus is the persistent sensation that you still need to pass stool even when little or nothing remains in the bowel.
The person may repeatedly feel:
“I still need to go.”
Yet when they reach the toilet, very little or nothing may pass. This occurs because inflammation of the rectum and colon continues stimulating the sensation of needing to evacuate.
Fatigue may become significant, particularly with extensive or active disease.
Several factors can contribute, including:
ongoing inflammation + blood loss + anemia + reduced intake + disturbed sleep + dehydration + nutritional problems.
Fatigue is especially associated with more extensive or severe ulcerative colitis.
During significant disease activity, patients may eat less because eating is associated with pain, urgency or diarrhea. Ongoing inflammation and frequent bowel movements can further contribute to unintended weight loss.
Weight loss and appetite loss are recognized symptoms of extensive/pancolitis.
Moderate-to-severe inflammation can produce fever. Fever together with very frequent bloody diarrhea, rapid heart rate, severe abdominal symptoms or marked weakness raises concern for severe disease and requires medical assessment.
Chronic intestinal blood loss and inflammation can lead to anemia. Iron-deficiency anemia and anemia associated with chronic inflammation can both occur in ulcerative colitis.
Possible manifestations include:
fatigue, weakness, dizziness, shortness of breath, paleness and reduced exercise tolerance.
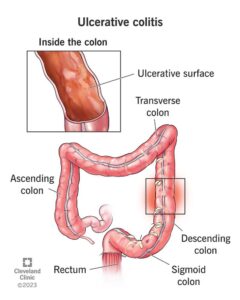
The colon consists of several layers. Ulcerative colitis primarily affects the innermost lining (mucosa) of the large intestine.
During active disease, this lining becomes inflamed and can develop small open ulcers.
Those damaged areas can bleed and release mucus or pus.
One important characteristic separates classic ulcerative colitis from Crohn’s disease.
With UC, inflammation generally starts at the rectum and extends continuously upward.
With pancolitis, that continuous inflammatory involvement extends through essentially the whole colon.
Crohn’s disease, by comparison, can affect different parts of the gastrointestinal tract and may leave normal areas between diseased areas. It can also penetrate more deeply through the bowel wall.
The exact cause of ulcerative colitis remains unknown.
Current evidence indicates that several factors interact, including:
**genetic susceptibility
It would therefore be medically inaccurate to describe pancolitis simply as being caused by “toxins,” stress, a particular food, parasites, or a single microbiome imbalance.
Stress and diet can certainly influence symptoms in some patients, but they have not been established as the underlying cause of ulcerative colitis.
An inflamed colon does not handle fluid normally. Inflammation also stimulates bowel activity.
The combination can result in:
reduced water reabsorption → faster bowel transit → frequent loose stools → diarrhea.
If diarrhea becomes severe, substantial fluid and electrolyte losses can occur.
The mucosal surface becomes inflamed and ulcerated. These damaged areas can bleed, resulting in blood mixed with stool or bloody diarrhea.
This is why persistent rectal bleeding should never simply be treated as a “detox reaction.” In someone with pancolitis, it can represent active inflammatory disease and ongoing blood loss.
Pancolitis usually does not remain at exactly the same level of activity continuously.
Patients can experience:
FLARE → active inflammation and symptoms
followed by:
REMISSION → symptoms substantially improve or disappear.
Remission can sometimes last months or years. Modern treatment aims not merely to suppress diarrhea but to achieve and maintain remission and, where possible, healing of the colon lining.
Because the entire colon is involved, disease burden can be substantial.
Complications of ulcerative colitis can include significant bleeding, dehydration, anemia, osteoporosis, blood clots, inflammation involving the joints/skin/eyes, and increased colorectal-cancer risk with long-standing extensive disease.
Rarely, severe inflammation can lead to dangerous complications such as toxic megacolon, perforation of the colon or fulminant ulcerative colitis. These are medical emergencies.
For that reason, if we build a Hadassah-style Pancolitis Protocol, I would strongly separate supportive nutrition/supplementation from medical treatment. I would not recommend stopping prescribed mesalamine, corticosteroids, biologics, immunomodulators or other IBD treatment without the treating gastroenterologist.
Urgent medical assessment is particularly important with heavy rectal bleeding, severe or rapidly worsening abdominal pain/distension, persistent fever, repeated vomiting/inability to drink, marked weakness/fainting, signs of severe dehydration, or extremely frequent bloody bowel movements. Severe ulcerative colitis can require hospitalization.
For diagnosis and assessment, clinicians may use blood tests, stool tests (including tests for infection and inflammatory markers such as fecal calprotectin), colonoscopy with biopsies, and sometimes imaging.
Because pancolitis involves the entire colon, active disease—especially a severe flare—should be managed with appropriate medical supervision. Extensive inflammation can lead to significant fluid loss, bleeding and systemic illness.
Particular caution is needed when there is:
Severe abdominal distension, intense pain, fever and rapidly worsening illness can indicate complications such as toxic megacolon or bowel perforation and require urgent medical care.
Frequent diarrhea can cause loss of water and electrolytes, including sodium and potassium. Severe losses can cause weakness, dizziness, muscle cramps, abnormal heart rhythms and kidney problems.
Hydration therefore becomes particularly important during active disease. However, simply drinking large quantities of plain water may not adequately replace significant electrolyte losses in severe diarrhea.
Repeated intestinal bleeding can contribute to iron-deficiency anemia, while chronic inflammation can also contribute to anemia through other mechanisms.
Monitoring may include a full blood count and, where clinically appropriate, iron/ferritin and other nutritional markers.
During prolonged or severe disease, reduced food intake, diarrhea, inflammation and medication effects can contribute to nutritional problems.
Depending on the individual and treatment history, clinicians may monitor nutrients such as iron, vitamin B12, folate and vitamin D, as well as overall nutritional status.
Importantly, deficiencies should ideally be identified rather than assuming that every person with pancolitis needs the same supplements.
Long-standing or severe ulcerative pancolitis can be associated with complications including severe bleeding, anemia, dehydration, toxic megacolon, bowel perforation, blood clots, osteoporosis and extra-intestinal inflammation affecting areas such as the joints, skin or eyes.
Another important long-term consideration is colorectal cancer risk. The risk increases with longer duration and greater extent of ulcerative colitis, particularly when inflammation has involved most or all of the colon. This is why people with longstanding extensive UC require an appropriate colonoscopy surveillance program under their gastroenterologist.
Discount Applied Successfully!
Your savings have been added to the cart.